Enloe Medical Center 340 W. East Ave, Chico CA 95973
Continuing Education
15 CEU Approved
Neck pain rarely lives where the patient points. The clinician who can separate myofascial from arthrogenic restriction in two minutes, who knows that C1 and C2 account for roughly half of cervical rotation and that cervical extension must translate to T3 and T4, treats a different patient than the one who treats the neck alone. Two days of hands-on instruction build that skill from the occiput to the mid-thoracic spine, the first rib, and the scapula, and send you home with a screen, a technique library, and a progression model ready for Monday morning.
Course Goals
Refine the differential diagnosis by distinguishing myofascial, arthrogenic, discogenic, neuromuscular, and visceral contributors to cervicothoracic pain.
Screen every patient quickly and safely using a validated review of systems, along with vascular, myelopathic, and ligamentous instability testing.
Localize the restricting tissue and the symptomatic segment during the first examination rather than over several visits.
Enhance treatment efficacy by pairing Dynamic Soft Tissue Mobilization with graded joint mobilization and immediate motor control loading.
Apply interregional dependency in practice: thoracic mobility, first rib position, scapular mechanics, and breathing pattern as drivers of neck pain.
Leave with an extensive clinical resource library of manual techniques, self-mobilizations, and graded exercise progressions, each with positioning detailed.
Defend every clinical decision with current systematic reviews and randomized controlled trials.
Course Objectives
Describe the functional anatomy, biomechanics, and normative segmental motion of the upper cervical, mid-cervical, cervicothoracic, and thoracic regions.
Screen for red flags using a standardized review of systems and identify vascular, neurological, systemic, and fracture presentations that contraindicate manual therapy.
Perform a complete cervicothoracic examination, including active, passive, resisted, neurological, palpatory, segmental joint-play, and provocation testing.
Perform Dynamic Soft Tissue Mobilization on the suboccipitals, sternocleidomastoid, scalenes, trapezius, levator scapulae, rhomboids, subscapularis, and pectoralis minor.
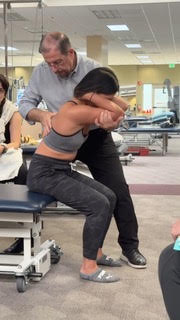
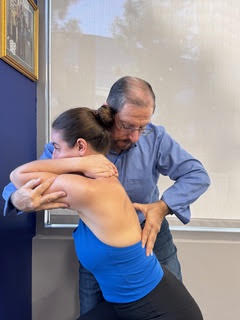
Apply graded joint mobilization to the occipito-atlantal, atlanto-axial, C2 to C7, first rib, costotransverse, and thoracic segments using three-dimensional positioning.
Prescribe progressive functional exercises for deep neck flexor endurance, cervical flexion and extension loading, scapulothoracic stabilization, and periscapular facilitation.
Integrate examination, manual therapy, and exercise into a documented treatment progression, demonstrated in timed clinical case drills.